New endowed lectureship investigates the role of the gut microbiome in obesity and diabetes

New endowed lectureship investigates the role of the gut microbiome in obesity and diabetes

New endowed lectureship investigates the role of the gut microbiome in obesity and diabetes

Thanks to the support of the Diabetes Center Berne (DCB), the University of Bern is establishing a new endowed lectureship at the Institute of Infectious Diseases (IFIK). Its aim is to investigate the role of the gut microbiome in metabolic diseases such as obesity, diabetes and related diseases and to develop new approaches to prevention and treatment. The lectureship is held by Prof. Dr. Maria Luisa Balmer.

Metabolic diseases such as obesity and type 2 diabetes have become one of the greatest global medical and social challenges in recent decades. Today, almost half a billion people worldwide live with diabetes – around a third of them are over 65 years old, but children and young people are also increasingly affected. By 2045, this figure is expected to rise further and reach well over 600 million people with the disease. The gut microbiota – i.e. the entirety of microorganisms in the gut – influences the metabolism and the immune system in a variety of ways. Disruptions in this delicate balance are considered a key factor in the development of obesity, type 2 diabetes and related metabolic diseases in humans.

A newly created lectureship will investigate the details of these interactions between metabolism and the immune system, as well as the mechanisms that could be used to develop new microbiome-based strategies for preventing and treating overweight and obesity. “The new endowed lectureship will strengthen a key future field of medicine, securing its place at our university in the long term,” says Virginia Richter, Rector of the University of Bern. Stephen Leib, Professor of Clinical Microbiology and Director of the Institute of Infectious Diseases (IFIK) at the University of Bern, where the endowed lectureship will be based, adds: “By integrating insights from basic research and clinical practice, new approaches to tackling obesity and diabetes can be developed. This could make a tangible contribution to addressing one of the most urgent health challenges of our time.”

Research at the interface of microbiota, immunology and metabolism

At the heart of the twelve-year lectureship, which is endowed with around five million Swiss francs, is research into immunometabolism – a relatively new field that investigates the interactions between metabolic processes and the immune system. A central working hypothesis is that in obesity and diabetes, certain metabolic products of the intestinal microbiome trigger or intensify persistent, mild inflammatory processes in the body, that are involved in the regulation of body weight. Conversely, other microbial metabolites appear to protect against such inflammatory responses.

The new endowed lectureship will be held by Prof. Dr. Maria Luisa Balmer. Balmer is SNSF-Excellenza Assistant Professor and research group leader of the Translational Immunometabolism Lab at the Institute of Infectious Diseases at the University of Bern. In her research, she investigates which microorganisms have a protective effect against such inflammatory reactions and could, in a sense, be harnessed as the body’s own means of regulating weight. The aim is to establish a scientific basis for innovative strategies to prevent and treat these major diseases.

Balmer combines innovative experimental systems – such as germ-free mouse models, i.e. mice that are raised entirely without microorganisms, including gut bacteria – with state-of-the-art multi-omics approaches and clinical studies in patients with obesity and diabetes. Multi-omics approaches integrate data at the gene, protein and metabolite levels to obtain the most comprehensive possible picture of the underlying biological processes. This makes it possible to first identify mechanisms of interaction between the gut microbiome and its host, as well as potentially beneficial metabolites, in the mouse model and then test their relevance directly in patients.

“The endowed lectureship allows us to systematically decipher the functional role of individual microorganisms and their metabolic products and translate them more quickly into clinical application,” says Leib. Balmer adds: “I am delighted that the new endowed lectureship will enable us to complement the IFIK’s existing strong profile in infection research by systematically investigating how beneficial gut bacteria and their metabolic products could protect against obesity and diabetes.”

Contribution to prevention, therapy and personalized medicine

The establishment of the endowed lectureship is made possible thanks to the financial support of the Diabetes Center Berne (DCB) – a private, independent Swiss foundation established in 2017 by entrepreneur Willy Michel with the aim of making life with diabetes easier. Derek Brandt, CEO of the Diabetes Center Berne, emphasizes: “Metabolic diseases such as obesity and diabetes are among the most common and cost-intensive diseases of our time. It is crucial for us that new scientific findings are translated into concrete approaches for prevention and treatment as quickly as possible. A better understanding of the gut microbiome opens up promising new possibilities here.”

The endowed lectureship should therefore help to close an existing gap between classical infection research and metabolic medicine and promote new interdisciplinary collaborations within the Faculty of Medicine. “This field of research is already well established at the University of Bern. With the endowed lectureship, we want to make a targeted contribution to developing promising approaches more quickly towards application – especially where new findings can specifically improve diabetes management,” says Brandt. In particular, new microbiota-based prevention and therapy approaches against obesity and its secondary diseases, a deepening of interdisciplinary cooperation within the university and with external partners as well as impulses for personalized medicine, for example through the use of microbial biomarkers for individual risk assessment, are expected.

Downloads

Contact:

Media Relations
University of Bern
Tel: +41 31 684 41 42
E-mail: medien@unibe.ch

Diabetes Center Berne
E-mail : medien@dcberne.com

About Maria Luisa Balmer

Prof. Dr. med. Maria Luisa Balmer is an immunologist and physician and heads the Translational Immunometabolism Lab at the Institute for Infectious Diseases at the University of Bern. Her research investigates how the gut microbiota, metabolism and immune system interact and contribute to the development of common diseases such as obesity and diabetes. She has been awarded an SNSF Eccellenza Professorial Fellowship and various other national and international grants for her excellent research. in 2023, Balmer also received the Marie Heim-Vögtlin Prize for outstanding young female researchers.

More information: https://www.ifik.unibe.ch/forschung/translational_immunometabolism___trim_lab___maria_balmer/index_ger.html


Institute for Infectious Diseases (IFIK)

The Institute of Infectious Diseases (IFIK) is part of the Faculty of Medicine of the University of Bern and combines the entire spectrum of clinical microbiology in teaching, research and diagnostic services in the fields of virology, bacteriology, mycology, parasitology and immunological infection analysis. The IFIK is home to the Biosafety Center, which supports research with highly pathogenic microorganisms and is designated as a “WHO Collaborating Center for Biosafety and Biosecurity”.  The IFIK performs national health care tasks within the framework of mandates from the Federal Office of Public Health (FOPH) as the National Reference Center for Pneumococci (NZPn) and the National Center for Antibiotic Resistance (anresis.ch).

More information: https://www.ifik.unibe.ch/


Diabetes Center Berne (DCB)

The Diabetes Center Berne (DCB) is a private, independent Swiss foundation established in 2017 with the aim of making life with diabetes easier. The DCB supports ideas and projects in the field of diabetes technology worldwide by providing expertise, access to clinical research facilities and its own laboratories, as well as financial resources. The aim is to work in partnership to bring them a big step closer to market maturity. The work of the DCB is not profit-oriented – the goal is new insights and innovations in diabetes management as well as a vibrant community.

More information: https://www.dcberne.com/de/

More recent news

Sign up for our newsletter
to receive the latest news.

* Pflichtfelder
DSGVO *

But could the same data tell us much more about a person's health than we currently realise?

A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

What did the researchers discover?

The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

Particularly interesting were the findings among people living with type 2 diabetes.

The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

For example:

  • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
  • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.
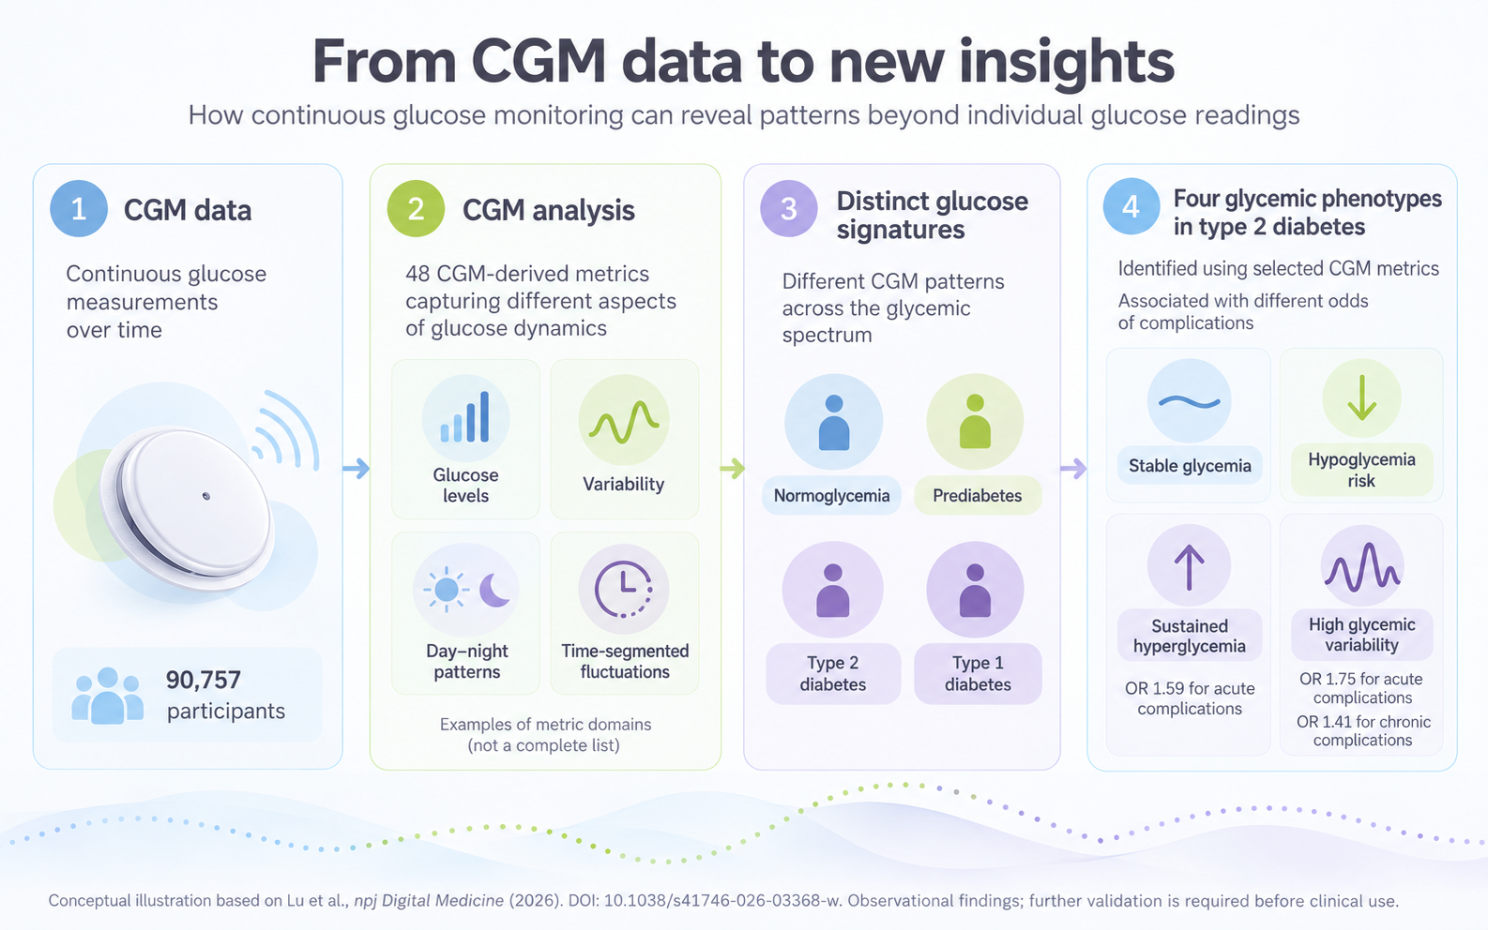
From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

What could this mean for diabetes care?

Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

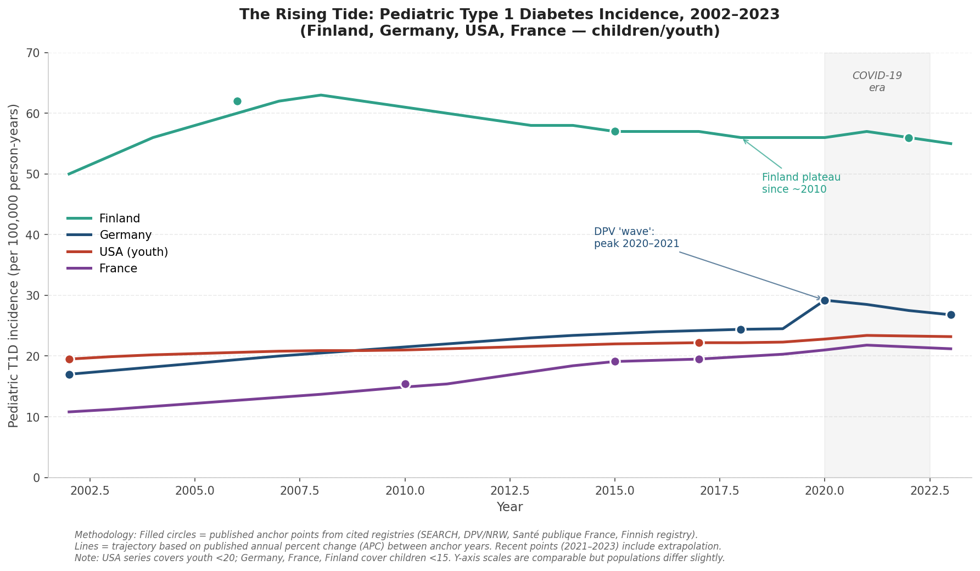
The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.
Projections to 2050

Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

Why is incidence rising?

T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

  • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
  • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
  • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
  • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
  • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

Implications for the next decade

Three practical implications stand out for health systems, innovators and the diabetes community:

  • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
  • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
  • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

At DCB, we see these trends as both a warning and a call to action.

The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

    Selected sources

    GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

    International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

    Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

    Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

    Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

    Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

    Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

    Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

    Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

    Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

    Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

    D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

    Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

    Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

    Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

    Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


    We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


    An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

    This post was previously published in Linkedin. Click here to see the original publication.

    DCB Research AG

    Freiburgstrasse 3
    3010 Bern
    Schweiz

    Four DCB professorships advance research in diabetes technology

    Four DCB professorships advance research in diabetes technology

    Four DCB professorships advance research in diabetes technology

    32 publications, 37 conference contributions and over CHF 6 million in research funding: the four professorships at the Diabetes Center Berne are advancing diabetes technology research and driving innovation in diabetes care. 

    The Diabetes Center Berne (DCB) is proud of the joint achievements of its four professors — Prof. Dr. Lilian Witthauer, Prof. Dr. Lisa Koch, Prof. Dr. Maria Louisa Balmer and Prof. Dr. José Garcia — and their teams. Together, the four professorships have built a highly productive research environment in recent years, driving innovation in diabetes technology and strengthening the international visibility of this field. 

    In 2025, the four DCB professorships jointly published or contributed to 32 scientific publications. These outputs reflect steadily growing scientific activity across the research portfolio and underline the relevance and quality of the work conducted within the DCB ecosystem. 

    In addition to publications, the teams delivered 37 contributions at national and international scientific conferences. These presentations play an important role in fostering exchange with the international research community, clinical partners and industry stakeholders in the field of diabetes technology. 

    The teams have also been successful in securing research funding: in recent years, the professorships have jointly raised more than CHF 6 million from competitive funding programmes, foundations and industry-supported research collaborations. These resources enable the development, validation and gradual translation of new technologies towards real-world application. 

    At the same time, the scientific environment around the four professorships has continued to grow. Today, a total of 61 researchers work across the DCB professorships, reflecting the dynamic development of the centre. The teams bring together expertise in science, engineering, clinical research and data science, creating an interdisciplinary environment for developing new solutions in diabetes care. 

    The Diabetes Center Berne is proud to provide a platform for this network of researchers. Through close collaboration between science, clinical practice and industry partners, the centre contributes to accelerating technological innovation and improving the lives of people living with diabetes. 

    More recent news

    Sign up for our newsletter
    to receive the latest news.

    * Pflichtfelder
    DSGVO *

    But could the same data tell us much more about a person's health than we currently realise?

    A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

    What did the researchers discover?

    The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

    Particularly interesting were the findings among people living with type 2 diabetes.

    The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

    For example:

    • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
    • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

    The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

    Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

    The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

    From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

    From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

    What could this mean for diabetes care?

    Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

    By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

    In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

    The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

    A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

    In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

    Projections to 2050

    Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

    For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

    Why is incidence rising?

    T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

    • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
    • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
    • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
    • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
    • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

    The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

    Implications for the next decade

    Three practical implications stand out for health systems, innovators and the diabetes community:

    • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
    • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
    • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

    At DCB, we see these trends as both a warning and a call to action.

    The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

    Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

      Selected sources

      GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

      International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

      Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

      Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

      Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

      Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

      Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

      Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

      Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

      Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

      Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

      D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

      Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

      Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

      Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

      Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


      We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


      An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

      This post was previously published in Linkedin. Click here to see the original publication.

      DCB Research AG

      Freiburgstrasse 3
      3010 Bern
      Schweiz

      SNAQ Launches the First AI Nutritionist for CGM Users Managing Diabetes

      SNAQ Launches the First AI Nutritionist for CGM Users Managing Diabetes

      SNAQ Launches the First AI Nutritionist for CGM Users Managing Diabetes

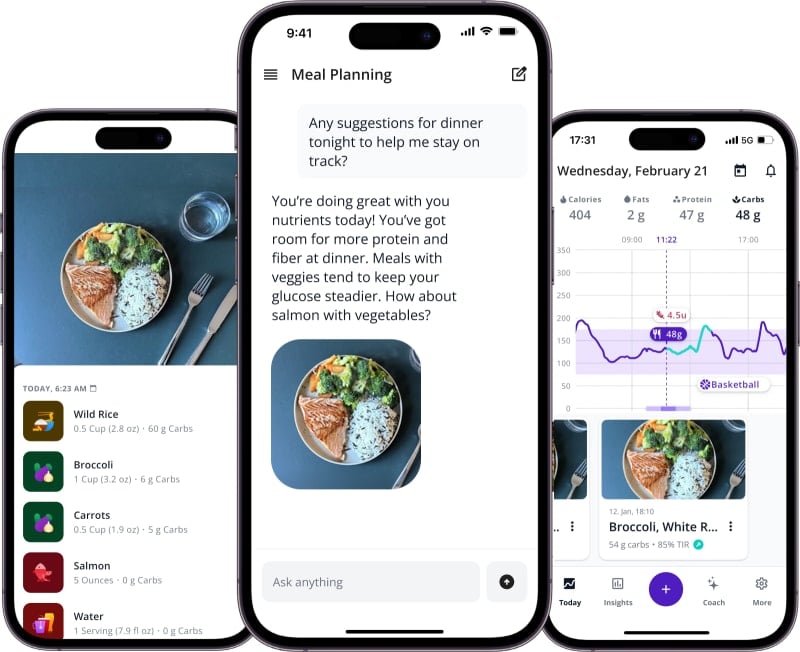
      SNAQ has announced the release of its AI Nutritionist, a first-of-its-kind digital companion designed to help people with diabetes.

      SNAQ has launched its AI Nutritionist, a digital companion designed to support people with diabetes through personalized, real-time nutrition guidance. By integrating meal analysis, glucose data, insulin, and activity tracking, the tool delivers tailored recommendations and always-on coaching to help users improve blood sugar control and build sustainable habits.

      Built on SNAQ’s clinically validated meal recognition technology, already used by over 250,000 people, the platform is supported by randomized-controlled evidence showing improved glycemic outcomes. CEO Aurelian Briner highlighted its potential to expand access to affordable, high-quality nutrition care globally. The AI Nutritionist is now available in the U.S., with international rollout planned throughout 2026.

      For more details, visit the full press release or explore SNAQ’s website to learn more about their AI-driven diabetes care solutions.

      More recent news

      Sign up for our newsletter
      to receive the latest news.

      * Pflichtfelder
      DSGVO *

      But could the same data tell us much more about a person's health than we currently realise?

      A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

      What did the researchers discover?

      The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

      Particularly interesting were the findings among people living with type 2 diabetes.

      The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

      For example:

      • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
      • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

      The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

      Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

      The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

      From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

      From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

      What could this mean for diabetes care?

      Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

      By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

      In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

      The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

      A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

      In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

      Projections to 2050

      Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

      For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

      Why is incidence rising?

      T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

      • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
      • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
      • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
      • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
      • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

      The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

      Implications for the next decade

      Three practical implications stand out for health systems, innovators and the diabetes community:

      • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
      • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
      • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

      At DCB, we see these trends as both a warning and a call to action.

      The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

      Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

        Selected sources

        GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

        International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

        Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

        Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

        Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

        Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

        Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

        Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

        Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

        Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

        Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

        D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

        Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

        Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

        Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

        Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


        We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


        An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

        This post was previously published in Linkedin. Click here to see the original publication.

        DCB Research AG

        Freiburgstrasse 3
        3010 Bern
        Schweiz

        DT-Report 2026: Join now

        DT-Report 2026: Join now

        DT-Report 2026: Join now

        The survey for the DT Report 2026 is now available – Take part and help shape the future of diabetes technology with us: Whether you are a person living with diabetes or a healthcare professional.

        Shape the Future of Diabetes Technology – Your Voice Matters!

        Together with diabetesschweiz, the Swiss Society for Endocrinology and Diabetology (SGED | SSED), and partner organizations in Germany and Austria, the DCB is conducting a representative survey on diabetes technology for the DT Report 2026.

        Why your participation matters:
        Your experiences and feedback are essential for improving the care and further development of diabetes technology in a targeted way. By taking part, you help make barriers and needs visible and create the foundation for future innovations.

        Take part now:

        Join us and make an important contribution to advancing diabetes technology and improving the quality of life for people with diabetes.

        More recent news

        Sign up for our newsletter
        to receive the latest news.

        * Pflichtfelder
        DSGVO *

        But could the same data tell us much more about a person's health than we currently realise?

        A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

        What did the researchers discover?

        The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

        Particularly interesting were the findings among people living with type 2 diabetes.

        The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

        For example:

        • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
        • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

        The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

        Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

        The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

        From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

        From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

        What could this mean for diabetes care?

        Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

        By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

        In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

        The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

        A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

        In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

        Projections to 2050

        Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

        For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

        Why is incidence rising?

        T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

        • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
        • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
        • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
        • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
        • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

        The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

        Implications for the next decade

        Three practical implications stand out for health systems, innovators and the diabetes community:

        • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
        • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
        • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

        At DCB, we see these trends as both a warning and a call to action.

        The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

        Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

          Selected sources

          GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

          International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

          Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

          Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

          Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

          Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

          Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

          Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

          Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

          Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

          Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

          D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

          Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

          Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

          Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

          Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


          We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


          An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

          This post was previously published in Linkedin. Click here to see the original publication.

          DCB Research AG

          Freiburgstrasse 3
          3010 Bern
          Schweiz
          Diabetes Center Berne @ BEA

          Diabetes Center Berne @ BEA

          Diabetes Center Berne @ BEA

          DCB joined the Focus Day at BEA in Bern, an event highlighting the latest in healthcare innovation. It was a great opportunity to showcase how Diabetes Center Berne is advancing projects that turn research into practical solutions for improving diabetes care.

          DC Berne BEA

          Speakers and participants had a great time at the Focus Day at BEA in Bern last Saturday! The event at the new Festhalle brought together innovators from across healthcare, with a spotlight on how we can improve patient care and drive digital medicine forward.

          A highlight for DCB was the presentation of CEO Derek Brandt, who shared the vision of Diabetes Center Berne. He emphasized how we are committed to improving the lives of people with diabetes through our cutting-edge translational projects.

          It was inspiring to be part of such a forward-thinking event, where healthcare leaders like Christoph Ammann, Simon Rothen, and others shared their insights on the future of medicine in Bern. A big thank you to everyone who contributed to making this event a success!

          Focusday at the BEA

          More recent news

          Sign up for our newsletter
          to receive the latest news.

          * Pflichtfelder
          DSGVO *

          But could the same data tell us much more about a person's health than we currently realise?

          A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

          What did the researchers discover?

          The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

          Particularly interesting were the findings among people living with type 2 diabetes.

          The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

          For example:

          • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
          • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

          The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

          Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

          The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

          From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

          From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

          What could this mean for diabetes care?

          Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

          By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

          In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

          The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

          A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

          In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

          Projections to 2050

          Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

          For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

          Why is incidence rising?

          T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

          • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
          • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
          • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
          • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
          • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

          The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

          Implications for the next decade

          Three practical implications stand out for health systems, innovators and the diabetes community:

          • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
          • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
          • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

          At DCB, we see these trends as both a warning and a call to action.

          The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

          Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

            Selected sources

            GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

            International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

            Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

            Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

            Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

            Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

            Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

            Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

            Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

            Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

            Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

            D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

            Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

            Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

            Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

            Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


            We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


            An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

            This post was previously published in Linkedin. Click here to see the original publication.

            DCB Research AG

            Freiburgstrasse 3
            3010 Bern
            Schweiz