DCB Newsletter #10/2023: Ending Diabetes Stigma? 

DCB Newsletter #10/2023: Ending Diabetes Stigma? 

Dear Community – We are happy to present to you the next episode of our series “DID YOU KNOW” in which we publish interesting facts about life with diabetes that you might not know yet. In this edition, we want to focus on stigma – or rather, on how we can work towards ending diabetes stigma. Enjoy the read!

“Did you eat too much sugar as a kid?”, “Should you really be eating that with diabetes?”, “Are you injecting drugs in public?” – These and similar questions often sound familiar to many people with diabetes, too often do they need to explain themselves and their condition to other people. In public media, diabetes is often depicted in a stigmatised way, fostering misconceptions and judgment in people who do not know much about life with diabetes. But also, people who should know – healthcare professionals and people in the diabetes community – are not exempt from exhibiting misconceptions and fostering stigma.  

Most people with diabetes have experienced stigma

In psychology, stigma is defined as “the negative social attitude attached to a characteristic of an individual that may be regarded as a mental, physical, or social deficiency. A stigma implies social disapproval and can lead unfairly to discrimination against and exclusion of the individual.” [1] Thus, diabetes stigma in particular discriminates people based on their condition and can lead to blame, rejection, or exclusion due to the perceived stigmatisation. 

Most people living with diabetes have experienced social stigma [2]. It can present itself in many ways and in different parts of their lives, whether it is in their private lives, in the medical field, at the workplace or in politics – and whether it is from outside or inside the community. It can be all-encompassing, from seemingly meaningless interactions with strangers in the street, to influencing political decisions and fostering systemic discrimination of those living with diabetes. 

Efforts on ending diabetes stigma in the community

In the past years, there have been many efforts in the diabetes community to develop guides on how to minimise diabetes stigma, especially by reflecting on the language we use. The in-depth guides, reflecting the international #languagematters movement are available online. Most importantly, the use of active first-person language is recommended (“people living with diabetes” instead of “diabetics”) and judgmental language (e.g. “failing to have control”, “non-compliant”,…) should be avoided as to not reinforce negative stereotypes. 

Life with diabetes is a 24/7 challenge and everyone is trying their best, so blame or judgment are not going to help anyone on their journey with diabetes – on the contrary, diabetes stigma is strongly related to psychological distress in people living with diabetes [3]. It has been shown to have negative effects on people’s mental and physical health, fostering diabetes distress and having negative impact on diabetes-related health outcomes such as Time in Range and HbA1c [4, 5]. It is crucial that diabetes stigma and the fight against it caption the attention of all of us – in medical treatment, product development, policy action and all interactions with all people living with diabetes. 

What can we do to end diabetes stigma?

Recently, the “international consensus recommendations to bring an end to diabetes stigma and discrimination” were developed by a group of 51 experts around the world and a campaign for the pledge to end diabetes stigma was launched [6]. 

The pledge identifies different actions needed to end diabetes stigma and discrimination:

  • “respecting people with all types of diabetes, 
  • recognising diabetes stigma exists and has harmful impacts, 
  • acknowledging and challenging my/our own prejudices about (people with) diabetes, 
  • using accurate, respectful, inclusive, non-judgmental, and strengths-based language, messaging, and imagery when communicating with or about people with diabetes, 
  • avoiding and challenging fear-based messaging and imagery, 
  • condemning discrimination due to diabetes and advocating for equal treatment and support for people with diabetes, 
  • encouraging initiatives, policies, and laws that promote equity for all people with diabetes.” [6]
     

Listening to those living with diabetes is crucial

    To truly #EndDiabetesStigma, it is crucial that we listen to those living with diabetes and experiencing it firsthand. That is why we believe in user- and patient-centric research and product development. Together, we can pro-actively work on the language and imagery we use to reflect diabetes. 

    At DCB, we have happily endorsed the pledge and we invite you to do the same. Let’s end diabetes stigma together! You can endorse the pledge now as an individual or an organisation: https://enddiabetesstigma.org/  


    Thanks so much for reading and we’ll provide you with the next episode of this series soon!

    Read more about the #languagematters movement and explore the international guides: https://www.languagemattersdiabetes.com/the-documents  

    [1] American Psychological Association. APA Dictionary of Psychology. American Psychological Association. https://dictionary.apa.org/stigma 

    [2] The Lancet Diabetes; Endocrinology. (2018). Diabetes stigma and discrimination: Finding the right words. The Lancet Diabetes; Endocrinology, 6(9), 673. https://doi.org/10.1016/s2213-8587(18)30235-3  

    [3] Guo, X., Wu, S., Tang, H., Li, Y., Dong, W., Lu, G., Liang, S., & Chen, C. (2023). The relationship between stigma and psychological distress among people with diabetes: A meta-analysis. BMC Psychology, 11(1). https://doi.org/10.1186/s40359-023-01292-2  

    [4] Hansen, U. M., Olesen, K., & Willaing, I. (2020). Diabetes stigma and its association with diabetes outcomes: A cross-sectional study of adults with type 1 diabetes. Scandinavian Journal of Public Health, 48(8), 855–861. https://doi.org/10.1177/1403494819862941  

     [5] Liu, N. F., Brown, A. S., Folias, A. E., Younge, M. F., Guzman, S. J., Close, K. L., & Wood, R. (2017). Stigma in people with type 1 or type 2 diabetes. Clinical Diabetes, 35(1), 27–34. https://doi.org/10.2337/cd16-0020 

    [6] End diabetes stigma and discrimination. https://enddiabetesstigma.org/ 

    This post was previously published in Linkedin. Click here to see the original publication.

    More recent news

    Sign up for our newsletter
    to receive the latest news.

    * Pflichtfelder
    DSGVO *

    But could the same data tell us much more about a person's health than we currently realise?

    A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

    What did the researchers discover?

    The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

    Particularly interesting were the findings among people living with type 2 diabetes.

    The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

    For example:

    • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
    • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

    The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

    Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

    The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.
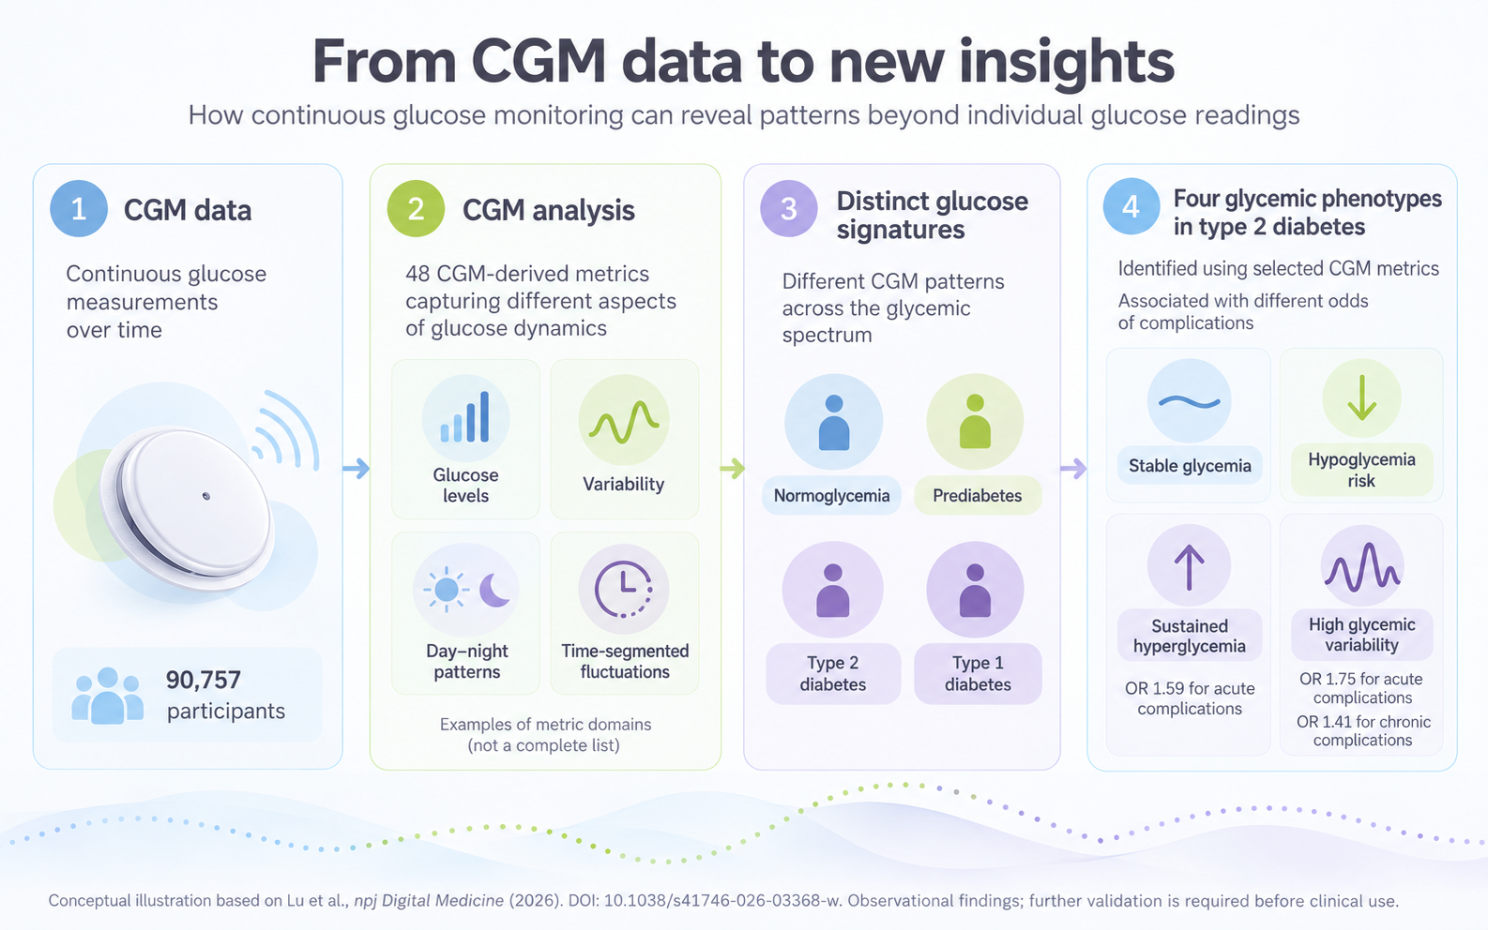
    From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

    From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

    What could this mean for diabetes care?

    Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

    By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

    In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

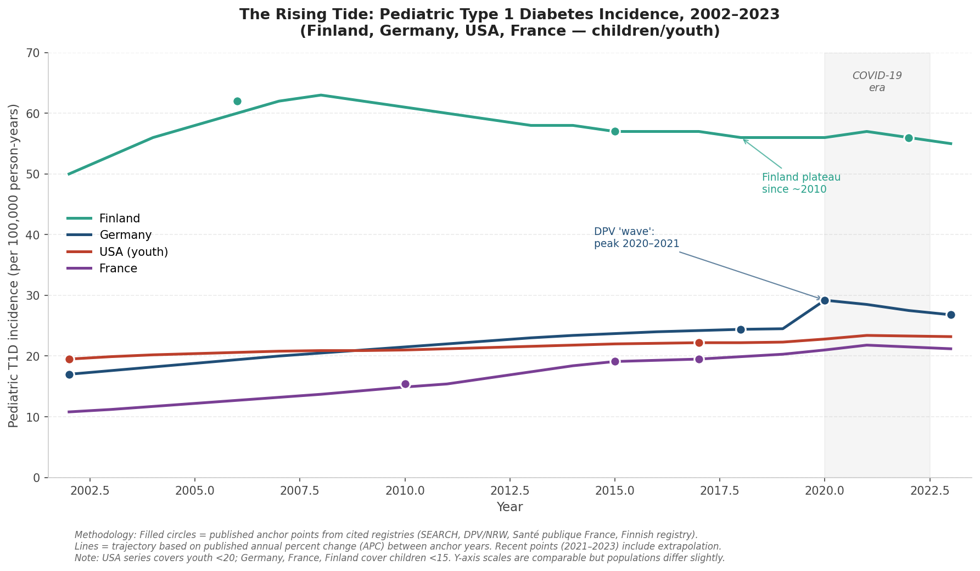
    The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

    A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

    In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.
    Projections to 2050

    Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

    For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

    Why is incidence rising?

    T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

    • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
    • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
    • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
    • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
    • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

    The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

    Implications for the next decade

    Three practical implications stand out for health systems, innovators and the diabetes community:

    • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
    • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
    • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

    At DCB, we see these trends as both a warning and a call to action.

    The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

    Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

      Selected sources

      GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

      International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

      Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

      Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

      Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

      Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

      Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

      Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

      Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

      Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

      Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

      D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

      Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

      Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

      Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

      Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


      We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


      An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

      This post was previously published in Linkedin. Click here to see the original publication.

      DCB Research AG

      Freiburgstrasse 3
      3010 Bern
      Schweiz

      DCB Innovation Challenge: Top 20 Digital Diabetes Solutions

      DCB Innovation Challenge: Top 20 Digital Diabetes Solutions

      DCB Innovation Challenge: Top 20 Digital Diabetes Solutions

      The competition was fierce, and the decisions were not easy, as our evaluation committee received an overwhelming number of outstanding submissions. But these innovative solutions stood out among a highly competitive field of participants, and we are delighted to present the TOP 20 Digital Diabetes solutions of the DCB Innovation Challenge 2023!

      Meet the top 20 digital solutions of the DCB Innovation Challenge

      Joycelyn Cornthwaite (US): JoyCare – Right Data, Right Time, Right Recommendations, for better maternal and fetal outcomes

      “JoyCare provides a fast, efficient, and easy to implement digitalization of the care process. Alerts support communications to clinicians and patients using existing methods such as EHR messaging, voice calls, and smartphone push. Data-driven escalation procedures along with tracking and auditing help to coordinate resources towards efficient and effective diabetes management.”

      Leonard Rinser (GER): GLAICE – Empowering Exercise in Diabetes

      “Our digital solution is based on an algorithm that transforms medical research into accessible and easy-to-understand recommendations that are adjusted to the daily lifestyle and tailored to each person’s metabolism. Through this data- and evidence-based approach, GLAICE empowers informed decision-making for everyone with diabetes, supporting you to lead a healthy, active, and self-determined life – anytime, anywhere, and with more ease.”

      Jazz Sethi (IN): Back to Basics – A 360 Degree Education Program for Type 1 Diabetes

      “India’s healthcare system is overburdened. To combat this, we launched our flagship education project for 1:1 counselling called BACK-TO-BASICS (B2B). Any individual living with T1D or an immediate stakeholder (caregiver, friends & family etc.) can virtually meet with our team of facilitators to navigate daily management, discuss unconventional topics and walkthrough our educational resources. We provide unlimited B2B sessions at no charge, in 9+ languages with a qualified professional, also living with T1D.”

      Mridula Kapil Bhargava (IN): CareOll – The Ultimate Patient Advocacy Platform where every voice matters

      “An innovative platform that gives voice to Lived experiences of People with Diabetes (and other medical conditions) to facilitate advocacy, qualitative research, first-of-its-kind health education through stories using graphics and animojis with verified disease-related content by experts and patient advocates, and Health-content Checker from social media & messaging platforms.”

      Jock Schulz (GER): Welshare Health – Take back control of your health data!

      “Take back control of your health data! We are building a tool for you to personalize how you share your health information. That way you can control who has access to it. Whether you get sick while traveling and want to share a certain part of your health record with a doctor or if you want to contribute to medical research- you deserve to choose how your own data is shared. And if you’re interested, you can even monetize your contribution to earn your share.”

      Katharine Kelly (UK): Spotlight-AQ − Improving Routine Diabetes Visits: Helping People with Diabetes Feel Heard and Doctors Feel Empowered to Care

      “Spotlight-AQ is a novel validated infographic assessment platform highlighting user priority concerns and immediate mapped resources to meet those unmet needs. Truly personalised healthcare. Deliverable by any healthcare professional, in any setting with any person with diabetes; Spotlight-AQ fits seamlessly within the constraints of existing healthcare systems and structures.”

      Rob Howe (US): The Diabetes Creator Collective from Diabetics Doing Things

      “Founded in 2015, Diabetics Doing Things empowers, informs and inspires people and creators living with diabetes through storytelling, events and community. The Diabetes Creator Collective will create a sustainable ecosystem for creators with diabetes to grow diabetes awareness, fight diabetes stigma and provide a chance for more creators with diabetes to earn a living doing what they do best.”

      Stephane Alberth (CH): Aixa – Your Digital Diabetes Guide and Coach

      “Enter “Aixa”, your Digital Diabetes Expert Coach. Aixa can provide support along the entire patient journey with a friendly face and warm supportive conversation. In summary, Aixa can integrate the best knowledge and understanding of patient needs to create natural, delightful patient conversations that support them when they need it most, while reducing the workload on the limited available health practitioners.”

      Bridget McNulty (SA): Solving diabetes education in Africa, using WhatsApp

      “Sweet Life has been creating easy-to-understand diabetes information for our community since we started in 2011, but over the past 3 years we’ve had a specific focus on testing out the most effective formats, language and languages (SA has 11 official languages). We now know how to solve diabetes education in South Africa and pave the way for it to be solved in Africa if we build the system in the right way. How? A WhatsApp chatbot.”

      Sam Royston (US):  Replica Health – A Search Engine & Conversational AI for T1D Data

      “We build an AI powered search engine for your metabolism, starting with an iOS app that allows diabetics to access their metabolic history to quickly answer questions relevant to their care. We’re working on a system that allows patients (and doctors) to ask detailed questions in plain English. Users receive answers directly via Large Language Models that infer what the user wants and triggers a corresponding analysis of data streams generated by medical devices and smartphones.”

      Susa Horvath (GER): ZenZen –  Empower Mothers, Nurture Future

      “The innovation of our product is to provide medical knowledge transfer with the help of a digital product to offer 24/7 available medical and emotional support to pregnant women with GDM. With the help of Generative AI technology, we can offer continuous support beyond the scope of traditional medical professional/patient relationships, addressing the full complexity of GDM, including areas such as mental health, exercise, and sleep.”

      Greg Badros (US): Gluroo – Collaborative Diabetes Logger

      “You already know how to use Gluroo: it’s a chat app! The messaging group is your GluCrew, and Gluroo provides high-quality integrations with CGMs (Dexcom, Libre, and also anything that writes CGM values into Apple HealthKit or Nightscout) and Pumps (DIY Loop, Omnipod 5, and also anything that writes into Apple HealthKit or Nightscout). Those integrations contribute to Gluroo’s diabetes Event Log – the GEL.  That GEL is shared and synchronized in real-time across all the devices so everyone can stay in sync, in real-time.”

      Alejandro Clarós (ES): Using the power of AI to Predict and Prevent Metabolic Syndrome and its Comorbidities

      “Higia’s AI solutions provide personalized healthcare by analyzing patient data from multiple sources to identify individual risk factors and predict the likelihood of developing certain conditions. This enables patients and healthcare professionals to take proactive measures to prevent or manage chronic diseases by providing tailored recommendations and intervention opportunities.”

      Gayathri Badrinath (US): Devyn – Simplifying Life with Gestational Diabetes

      “We have developed a first-of-its kind mobile app for GDM that drastically simplifies the patient experience associated with daily self-monitoring during pregnancy and keeps women  in control of their care journey. Our early results are exceptional with extremely high engagement rates.  After pregnancy, we aim to connect our users with medical experts in women’s cardiometabolic health through a virtual visit.”

      Leo Rifkind (UK): Huddle Health – Achieving Improved Diabetes Health Outcomes by Evidence-Based Mental Health Therapy

      “Huddle Health will be a mobile application that facilitates improved physical health outcomes in diabetes via mental health strategies. It will have a desktop dashboard for Huddle Health administration and Providers to track their patients and carry out appointments.”

      Matt Payne (US): No More “Ozempic Butt” – Metabolic Lifestyle Therapy For GLP-1

      “Our idea is to complement diabetes and obesity medications like Ozempic and Wegovy with a metabolic support program delivered digitally.”

      Jayne Budd (UK): Know your risk of CKD with CSP!

      “The CKD Screening Prioritizer (CSP) is digital software that contains an intelligent risk calculator. The healthcare professional can access it via our web portal, or it can be integrated into electronic medical records systems.  It is designed to support targeted Chronic Kidney Disease (CKD) screening (eGFR diagnosis) stratifying the patients by risk so that those most at risk are sent for diagnosis allowing for more efficient resource allocation.”

      Elena Paraschiv (RO): Glyco – Your Path to Optimal Diabetes Wellness

      “Introducing Glyco, the innovative diabetes management app that’s changing the game. Our app offers a comprehensive solution that goes beyond traditional diabetes management tools, providing users with personalized recommendations, nutrition management, mental health support, complication screening telemedicine, and more. Our cutting-edge app integrates a suite of features that make it easy for users to manage their blood glucose levels, stay on top of their nutrition, connect with medical professionals when needed and support networks.”

      Robert Maurer (US): The right drug for the right patient – enabling delivery of standard of care drug selection in routine practice

      “We have developed a commercially available analytical report, based on our living expert system reporting platform, which provides physicians with guidance to aid in choosing the optimal treatment regimen for diabetes patients. In addition to glucose control, the TIGAR™ report incorporates insulin resistance, beta-cell condition, cardiovascular disease and kidney condition, all of which impact diabetes care. The result of this personalized therapy is that everyone wins in the first year– doctor, patient, payer, and lab.”

      Inka Benthin (GER): GlucoFit – Digital assistant for optimizing insulin therapy

      “Introducing GlucoFit, the blood sugar management navigation system that provides automatic and timely information, to free individuals from constantly thinking about their diabetes. By intelligently integrating existing data, GlucoFitidentifies the causes of recurring highs and lows in blood sugar levels and derives actionable advice about therapy adjustments. With a patient-centered approach, this innovative application strengthens therapy adherence and promotes long-term health.”

      Download the PDF Overview

      More recent news

      Sign up for our newsletter
      to receive the latest news.

      * Pflichtfelder
      DSGVO *

      But could the same data tell us much more about a person's health than we currently realise?

      A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

      What did the researchers discover?

      The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

      Particularly interesting were the findings among people living with type 2 diabetes.

      The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

      For example:

      • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
      • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

      The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

      Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

      The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

      From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

      From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

      What could this mean for diabetes care?

      Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

      By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

      In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

      The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

      A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

      In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

      Projections to 2050

      Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

      For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

      Why is incidence rising?

      T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

      • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
      • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
      • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
      • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
      • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

      The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

      Implications for the next decade

      Three practical implications stand out for health systems, innovators and the diabetes community:

      • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
      • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
      • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

      At DCB, we see these trends as both a warning and a call to action.

      The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

      Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

        Selected sources

        GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

        International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

        Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

        Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

        Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

        Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

        Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

        Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

        Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

        Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

        Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

        D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

        Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

        Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

        Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

        Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


        We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


        An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

        This post was previously published in Linkedin. Click here to see the original publication.

        DCB Research AG

        Freiburgstrasse 3
        3010 Bern
        Schweiz

        DCB Newsletter #9/23: Interview with José García-Tirado

        DCB Newsletter #9/23: Interview with José García-Tirado

        Dear Community – we are thrilled to present you with the next episode of our series “INSIDE DCB” – this time, with an interview with José García-Tirado. Enjoy the read!

        Since the beginning of 2023, José García-Tirado has been a professor specialising in diabetes technology at the University Department of Diabetology, Endocrinology, Nutritional Medicine and Metabolism (UDEM) and at the DCB (Diabetes Center Berne). Together with his team, he is involved in the development of even more precise therapies such as closed-loop systems for people with diabetes and other metabolic diseases.

        José, what is your research about?

        In our research, we are investigating the effects of type 1 diabetes and how we can develop technological solutions to better manage glucose in the body. We use computer models to understand different aspects of metabolism. Part of our work involves developing automated systems that deliver insulin like a fully functioning pancreas. We test these ideas on the computer and in clinical trials to ultimately make them useful for people with diabetes.

        What motivates you to work in the field of diabetes technology? How did you get involved in this topic?

        I am an engineer, was diagnosed with type 1 diabetes myself 10 years ago and had to overcome some hurdles, like most people with this disease. Coincidentally, I was attending a conference on the subject a few months later when I had an “aha” moment. I realized that I needed to get involved with the topic and contribute to the advancement of the field.

        This has inspired me to research better technologies for diabetes management. I find it exciting to turn complex ideas into practical solutions and help other people with diabetes.

        What is your biggest challenge as a professor?

        Being a professor nowadays takes most of your energy and thoughts every day. Balancing my passion and work with family/hobbies time proves to be very challenging. From the work perspective, being the leader of a research group demands constant planning, supervision of human resources, and progress evaluation. Making plans to work in this field also entails close collaboration with experienced medical doctors and knowing very well the regulatory pathways to working with human beings in an ethical and caring way.

        Professor Dr. José García-Tirado. Assistant professor with tenure track in diabetes technology.

        What goals do you want to achieve with your team and your lab, the PrecisionLab?

        Our goal is to develop technologies that can better support people with type 1 diabetes. We not only want to manage blood sugar, but also reduce other health risks. To this end, we are investigating new therapies and developing intelligent algorithms for insulin pumps.

        What projects are you currently researching and how can they make life easier for people with diabetes?

        The first project deals with the construction of an algorithm deployment platform in collaboration with Universitat Politècnica de Valencia. Such a platform will allow us to test every AID (“automated insulin delivery”) design in a clinical setting.

        The second project is the design and testing of the actual smart algorithm to modulate insulin from an insulin pump for people with type 1 diabetes. Such an algorithm will be deployed and tested in our algorithm deployment platform. To do so, we need to go through a rigorous regulatory process with Swiss Medic. After approval, we will test our algorithm on five (5) participants with T1D with real-life challenges.

        The third project relates to the understanding and mathematical modeling of macronutrient (carbohydrates, fats, and proteins) absorption in the bloodstream and how different compositions of meals affect glucose absorption.

        Where do you hope your research field will be in 5-10 years? What is your vision ?

        In the next few years, diabetes management technologies will evolve, with better sensors and insulin preparations. There is even the possibility of developing implantable systems that are even more similar to a pancreas. Similarly, we need to develop more accessible technologies for people with type 1 diabetes, as current options are often expensive and unavailable in many countries.

        All these advances can significantly improve the quality of life of people with diabetes.

        About José García-Tirado

        José García-Tirado is an Assistant Professor of Smart Algorithms in Diabetes Technology at the University of Bern. He has a B.Sc. from the Universidad Nacional de Colombia, a M.Sc. from CINVESTAV (Mexico), and a Ph.D. from the Universidad Nacional de Colombia, all in the field of control systems engineering. He later did a postdoctoral fellowship at the Rheinisch-Westfälische Technische Hochschule Aachen (RWTH Aachen) in 2013 and from 2017-2021 at the University of Virginia where he specialized in advanced control strategies for AID systems. Prof. García-Tirado has been faculty in three countries, at the Instituto Tecnológico Metropolitano (2014-2017 – Medellin, Colombia), University of Virginia (2021-2023, Charlottesville, US), and University of Bern (2023).


        Thanks so much for reading and we’ll provide you with the next episode of this series soon!

        This post was previously published in Linkedin. Click here to see the original publication.

        More recent news

        Sign up for our newsletter
        to receive the latest news.

        * Pflichtfelder
        DSGVO *

        But could the same data tell us much more about a person's health than we currently realise?

        A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

        What did the researchers discover?

        The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

        Particularly interesting were the findings among people living with type 2 diabetes.

        The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

        For example:

        • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
        • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

        The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

        Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

        The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

        From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

        From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

        What could this mean for diabetes care?

        Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

        By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

        In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

        The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

        A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

        In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

        Projections to 2050

        Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

        For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

        Why is incidence rising?

        T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

        • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
        • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
        • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
        • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
        • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

        The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

        Implications for the next decade

        Three practical implications stand out for health systems, innovators and the diabetes community:

        • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
        • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
        • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

        At DCB, we see these trends as both a warning and a call to action.

        The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

        Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

          Selected sources

          GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

          International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

          Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

          Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

          Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

          Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

          Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

          Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

          Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

          Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

          Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

          D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

          Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

          Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

          Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

          Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


          We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


          An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

          This post was previously published in Linkedin. Click here to see the original publication.

          DCB Research AG

          Freiburgstrasse 3
          3010 Bern
          Schweiz

          Research Participation Opportunities: New Studies “VOCircle” and “Moonwalk”

          Research Participation Opportunities: New Studies “VOCircle” and “Moonwalk”

          Research Participation Opportunities: New Studies “VOCircle” and “Moonwalk”

          Join us in fostering state-of-the art diabetes research! The DCB-associated research group from the Sensing & Monitoring Lab is currently looking for study participants both with and without diabetes. Read more about the opportunities below.

          Become Part of New Diabetes Research

          The DCB-associated research group from the Sensing & Monitoring Lab is currently looking for study participants with and without diabetes. The two new studies will shine a light on the circadian rhythm of volatile organic compounds as well as movements during nightly blood glucose fluctuations in people with diabetes. This is a great opportunity to become part of the science behind the diabetes management of tomorrow.

          The VOCircle Study

          The VOCircle study aims to research the circadian rhythm in volatile organic compounds (VOC). It is being conducted in Berne, Switzerland, and you will need to be present for about 8 hours.

          You are elligible if you
          1) don’t have any type of diabetes,
          2) have been living with
          type 1 diabetes for more than a year, or
          3) live with
          type 2 diabetes and use medication to treat it. 

          You can read more about it in the VOCircle Study Information.

          The Moonwalk Study

          The Moonwalk study aims to analyse movements during nightly blood glucose fluctuations.

          You are elligible if you live with diabetes, use insulin to manage your blood glucose levels and live near Berne, Switzerland. If you are elligible, the study will accompany you during 10 +/- 5 days and you will receive a compensation of 200 CHF.

          You can read more about it in the Moonwalk Study Information.

          Downloads

          Contacts

          Cléo Nicolier (VOCircle)

          cleo.nicolier@unibe.ch

          +41 (0) 76 250 17 76

          Camilo Mendez Schneider (Moonwalk)

          camilo.mendezschneider@unibe.ch

          +41 (0) 31 664 25 27

          More recent news

          Sign up for our newsletter
          to receive the latest news.

          * Pflichtfelder
          DSGVO *

          But could the same data tell us much more about a person's health than we currently realise?

          A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

          What did the researchers discover?

          The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

          Particularly interesting were the findings among people living with type 2 diabetes.

          The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

          For example:

          • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
          • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

          The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

          Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

          The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

          From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

          From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

          What could this mean for diabetes care?

          Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

          By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

          In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

          The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

          A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

          In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

          Projections to 2050

          Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

          For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

          Why is incidence rising?

          T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

          • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
          • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
          • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
          • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
          • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

          The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

          Implications for the next decade

          Three practical implications stand out for health systems, innovators and the diabetes community:

          • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
          • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
          • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

          At DCB, we see these trends as both a warning and a call to action.

          The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

          Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

            Selected sources

            GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

            International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

            Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

            Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

            Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

            Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

            Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

            Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

            Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

            Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

            Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

            D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

            Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

            Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

            Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

            Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


            We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


            An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

            This post was previously published in Linkedin. Click here to see the original publication.

            DCB Research AG

            Freiburgstrasse 3
            3010 Bern
            Schweiz