

Hot Off the Press: The DCB Annual Report 2023/24 is Out!

Hot Off the Press: The DCB Annual Report 2023/24 is Out!

Hot Off the Press: The DCB Annual Report 2023/24 is Out!

The fiscal year 2023/24 was a year marked by major milestones and remarkable progress for the Diabetes Center Berne (DCB), thanks to the great commitment of all employees. The DCB Annual Report has now been published and you can read more about the projects, teams, and their achievements of 2023/24.

The DCB – An Internationally Recognised Centre for Diabetes Technology

DCB is proud to have successfully completed their first large-scale projects. One highlight is the third edition of the Open Innovation Challenge 2023, which took their total number of partnerships with start-ups to around 100 start-ups from over 30 different countries.

Furthermore, Professor Lilian Witthauer and her team in the field of smart sensing along with Professor José Garcia-Tirado in the field of closed-loop systems are working on projects to improve the lives of people with diabetes. These initiatives exemplify how DCB effectively translates research findings into practical applications. Since April 2024, Professor Lisa Koch has also joined DCB, bringing her expertise in data analysis and artificial intelligence.

Special thanks go to the Advisory Board and patron Willy Michel, whose support enables DCB to position itself as an international center of excellence in diabetes technology.

Download the full report now!

Download the full report now!

Sign up for our newsletter
to receive the latest news.

* Pflichtfelder
DSGVO *

But could the same data tell us much more about a person's health than we currently realise?

A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

What did the researchers discover?

The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

Particularly interesting were the findings among people living with type 2 diabetes.

The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

For example:

  • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
  • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.
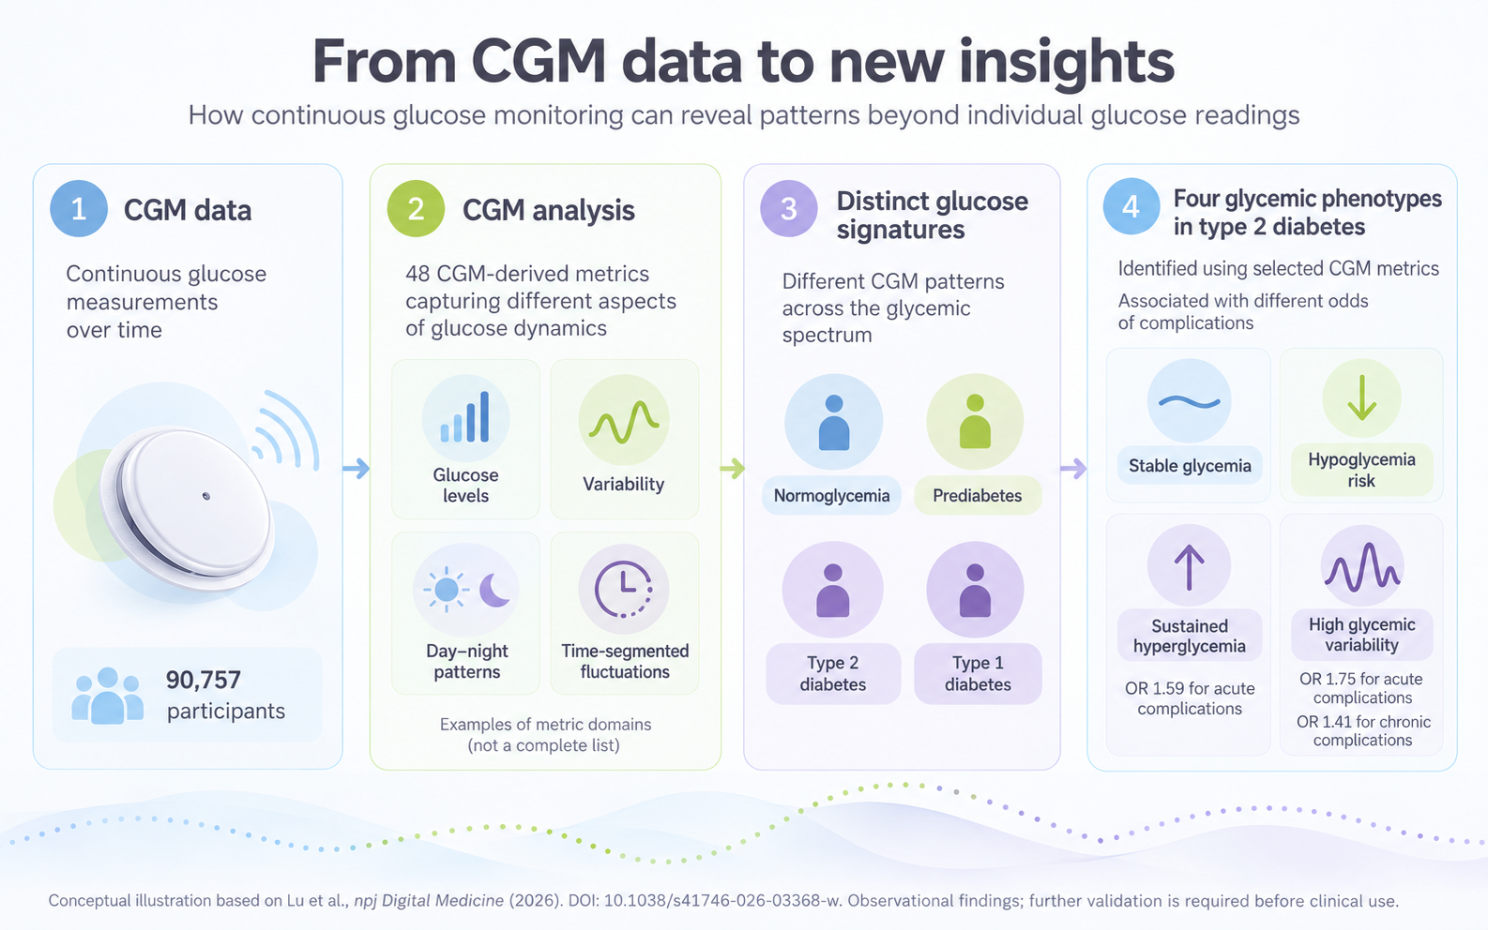
From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

What could this mean for diabetes care?

Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

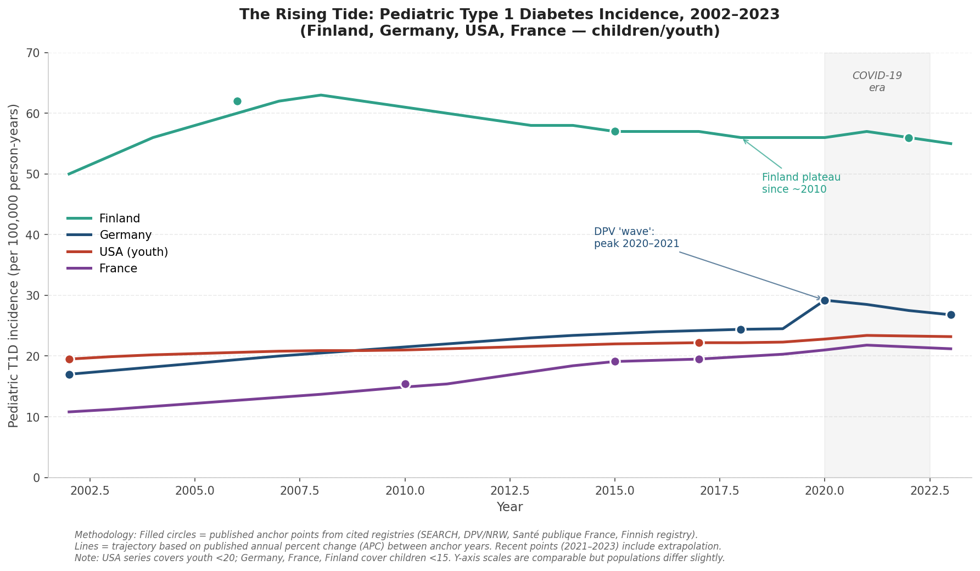
The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.
Projections to 2050

Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

Why is incidence rising?

T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

  • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
  • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
  • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
  • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
  • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

Implications for the next decade

Three practical implications stand out for health systems, innovators and the diabetes community:

  • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
  • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
  • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

At DCB, we see these trends as both a warning and a call to action.

The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

    Selected sources

    GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

    International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

    Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

    Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

    Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

    Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

    Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

    Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

    Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

    Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

    Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

    D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

    Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

    Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

    Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

    Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


    We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


    An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

    This post was previously published in Linkedin. Click here to see the original publication.

    DCB Research AG

    Freiburgstrasse 3
    3010 Bern
    Schweiz

    DCB featured in Nature Portfolio: “Cutting-edge diabetes technology to make lives easier”

    DCB featured in Nature Portfolio: “Cutting-edge diabetes technology to make lives easier”

    DCB featured in Nature Portfolio: “Cutting-edge diabetes technology to make lives easier”

    DCB is thrilled to be featured in the Nature Portfolio Spotlight on Switzerland. The article “Cutting-edge diabetes technology to make lives easier” dives into our work at DCB and outlines significant advancements in diabetes management.

    Cutting-edge diabetes technology to make lives easier

    The renowned Nature Portfolio has issued a Spotlight on Switzerland with the motto: “Switzerland has enjoyed a warm relationship with the rest of Europe for decades – but how has that influenced the research done in the country?”

    DCB is thrilled to be featured in this Spotlight, shining a light on diabetes technology research and innovation.

    Our assistant professors José García-Tirado and Lilian Witthauer, as well as our scientific program manager Martina Rothenbühler were interviewed, providing insights into their work at DCB and the development of technologies such as the artificial pancreas, which promises to transform the daily lives of people with diabetes by simplifying insulin management.

    “Our mission is to support diabetes research and technological advancement. We’re building bridges between research and startups, industry and other stakeholders.”

    – Martina Rothenbühler, DCB

    Read the article now to dive deeper into our work and see how innovative technologies are shaping the future of diabetes management.

    More recent news

    Meet us at ATTD!

    Meet us at ATTD!

    The ATTD congress in Barcelona is just around the corner and different members of the DCB team will be on-site. Meet...

    Sign up for our newsletter
    to receive the latest news.

    * Pflichtfelder
    DSGVO *

    But could the same data tell us much more about a person's health than we currently realise?

    A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

    What did the researchers discover?

    The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

    Particularly interesting were the findings among people living with type 2 diabetes.

    The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

    For example:

    • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
    • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

    The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

    Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

    The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

    From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

    From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

    What could this mean for diabetes care?

    Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

    By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

    In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

    The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

    A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

    In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

    Projections to 2050

    Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

    For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

    Why is incidence rising?

    T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

    • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
    • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
    • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
    • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
    • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

    The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

    Implications for the next decade

    Three practical implications stand out for health systems, innovators and the diabetes community:

    • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
    • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
    • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

    At DCB, we see these trends as both a warning and a call to action.

    The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

    Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

      Selected sources

      GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

      International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

      Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

      Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

      Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

      Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

      Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

      Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

      Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

      Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

      Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

      D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

      Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

      Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

      Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

      Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


      We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


      An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

      This post was previously published in Linkedin. Click here to see the original publication.

      DCB Research AG

      Freiburgstrasse 3
      3010 Bern
      Schweiz

      The DCB Open Innovation Challenge is Back: Submit Your Idea Now!

      The DCB Open Innovation Challenge is Back: Submit Your Idea Now!

      The DCB Open Innovation Challenge is Back: Submit Your Idea Now!

      For the fourth time, the Diabetes Center Berne is launching the Open Innovation Challenge with the aim of specifically promoting innovative projects in the field of diabetes management on Swiss and international level. Participating innovtors benefit from professional expert feedback, and the six best projects receive access to a bootcamp. The finalists will receive prize money of up to USD 100,000 and further support from the DCB. The DCB Innovation Challenge is the world’s largest diabetes technology award with international appeal.

      Can Your Idea Change Diabetes Management?

      More than 537 million people worldwide live with diabetes, which means a constant challenge in everyday life for those affected. Technological innovations make an important contribution to making it easier to deal with diabetes – whether it is measuring glucose levels, planning the amount of insulin needed via an app or even using automated insulin delivery systems. But despite these enormous advances in diabetes technology, there is still a great, unmet need for innovative technical solutions. These should help to ease the challenge for users in everyday life and improve the lives of people with diabetes in the long term.

      The DCB Open Innovation Challenge was initiated in 2021 with the aim of closing these gaps in diabetes technology with translational research. The goal of the challenge is to identify unique solutions which can make life easier for people with diabetes. Whether you’re a researcher, healthcare professional, start-up founder, or someone living with diabetes, your ideas are invaluable to us. We’re seeking diverse perspectives and innovative solutions to enhance the quality of life for individuals with diabetes.


      ​What’s in it for you?

      After a first round and feedback from the expert jury, the top 20 will enter a mentoring program. Two US-based innovators and four innovators from the rest of the world will be invited to an individually tailored bootcamp in the picturesque Swiss alps and will then pitch their final ideas at the grand DCB Start-Up Night in Berne, Switzerland, on 3 October 2024. Additionally, all finalists have the opportunity to present their ideas at the Diabetes Technology Meeting in the US on 15–17 October 2024.​

      The winning project will be selected by an international expert jury and rewarded with USD 100,000 in funding and in-kind support – making the DCB Open Innovation Challenge the world’s largest diabetes technology award with international appeal. You will get access to a global network of experts from the field – all while your idea remains entirely yours.

      Don’t miss out on this unparalleled opportunity to turn your idea into reality. Submit your idea by April 30 at our innovation platform innovation.dcberne.com

      More recent news

      Meet us at ATTD!

      Meet us at ATTD!

      The ATTD congress in Barcelona is just around the corner and different members of the DCB team will be on-site. Meet...

      Sign up for our newsletter
      to receive the latest news.

      * Pflichtfelder
      DSGVO *

      But could the same data tell us much more about a person's health than we currently realise?

      A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

      What did the researchers discover?

      The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

      Particularly interesting were the findings among people living with type 2 diabetes.

      The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

      For example:

      • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
      • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

      The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

      Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

      The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

      From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

      From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

      What could this mean for diabetes care?

      Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

      By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

      In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

      The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

      A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

      In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

      Projections to 2050

      Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

      For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

      Why is incidence rising?

      T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

      • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
      • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
      • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
      • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
      • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

      The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

      Implications for the next decade

      Three practical implications stand out for health systems, innovators and the diabetes community:

      • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
      • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
      • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

      At DCB, we see these trends as both a warning and a call to action.

      The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

      Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

        Selected sources

        GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

        International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

        Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

        Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

        Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

        Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

        Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

        Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

        Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

        Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

        Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

        D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

        Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

        Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

        Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

        Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


        We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


        An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

        This post was previously published in Linkedin. Click here to see the original publication.

        DCB Research AG

        Freiburgstrasse 3
        3010 Bern
        Schweiz

        Lisa Koch joins DCB as professor specialising in artificial intelligence and data science

        Lisa Koch joins DCB as professor specialising in artificial intelligence and data science

        Lisa Koch joins DCB as professor specialising in artificial intelligence and data science

        The newly created assistant professorship with tenure track is the third of a total of three professorships in the field of “Diabetes Technology and Artificial Pancreas” jointly created by the University of Bern, the Inselgruppe and the Diabetes Center Berne (DCB).

        Background in developing data science products for medical devices

        Before taking up her new position, Lisa Koch worked on machine learning for biomedical data analysis. She has a background in academic research as well as developing data science products for medical devices, with a strong focus on technology that can ultimately benefit people’s health in a safe and trustworthy way.

        After an undergraduate degree in electrical (BSc) and biomedical engineering (MSc) at ETH Zürich, Switzerland, Lisa Koch did a PhD in machine learning for medical image analysis at Imperial College London, UK.  After a post-doc at ETH Zürich, she joined the Swiss wearable medical device startup Ava, where she eventually became the data science team lead. In this position, she came to appreciate the need for demonstrably safe machine learning in healthcare.

        Safe, reliable, and effective data science tools
        In 2021, Lisa Koch returned to academic research to pursue research on this topic as a group leader for machine learning in medical diagnostics at the Hertie Institute for AI in Brain Health at the University of Tübingen, Germany. In her new role as assistant professor at the University of Bern, her long-term goal is to develop certifiably safe, reliable, and effective data science tools for patient-specific treatment systems in diabetes care.

        “With my research, I strive to deliver trustworthy AI-enabled diabetes care that provides real benefit to patients and clinicians. I am thrilled to join the cross-disciplinary ecosystem at the Diabetes Center Berne and the University of Bern Clinic for Diabetology, Endocrinology, Nutritional Medicine and Metabolism (UDEM), an ideal environment to advance this vision” says Koch.

        Derek Brandt, CEO of the DCB adds: “In addition to Lilian Witthauer, professor in the field of sensor technology, and José Garcia Tirado, professor for technology-assisted precision medicine, we have taken a third and important step with Professor Koch for the topic of artificial intelligence (AI) and data science in diabetes care. This enables us to further strengthen our international pioneering role in the field of translational diabetes technology research. We will continue doing everything we can to improve daily life for people with diabetes”.

        Lisa Koch

        Downloads

        More recent news

        Meet us at ATTD!

        Meet us at ATTD!

        The ATTD congress in Barcelona is just around the corner and different members of the DCB team will be on-site. Meet...

        Sign up for our newsletter
        to receive the latest news.

        * Pflichtfelder
        DSGVO *

        But could the same data tell us much more about a person's health than we currently realise?

        A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

        What did the researchers discover?

        The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

        Particularly interesting were the findings among people living with type 2 diabetes.

        The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

        For example:

        • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
        • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

        The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

        Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

        The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

        From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

        From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

        What could this mean for diabetes care?

        Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

        By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

        In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

        The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

        A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

        In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

        Projections to 2050

        Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

        For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

        Why is incidence rising?

        T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

        • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
        • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
        • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
        • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
        • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

        The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

        Implications for the next decade

        Three practical implications stand out for health systems, innovators and the diabetes community:

        • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
        • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
        • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

        At DCB, we see these trends as both a warning and a call to action.

        The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

        Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

          Selected sources

          GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

          International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

          Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

          Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

          Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

          Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

          Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

          Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

          Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

          Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

          Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

          D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

          Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

          Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

          Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

          Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


          We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


          An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

          This post was previously published in Linkedin. Click here to see the original publication.

          Diabetes Center Berne and Diabetes Technology Society Collaborate for the 2024 DCB Open Innovation Challenge

          Diabetes Center Berne and Diabetes Technology Society Collaborate for the 2024 DCB Open Innovation Challenge

          Diabetes Center Berne and Diabetes Technology Society Collaborate for the 2024 DCB Open Innovation Challenge

          We are very excited to announce the launch of the 2024 DCB Open Innovation Challenge for 1 April 2024, this year in collaboration with the Diabetes Technology Society!

          Can Your Idea Change Diabetes Management Forever?

          We are excited to announce the collaboration of the Diabetes Center Berne and the Diabetes Technology Society for the 2024 DCB Open Innovation Challenge, launching on 1 April 2024.​

          The DCB Open Innovation Challenge was initiated in 2021 and is the largest innovation challenge in the field of diabetes technology. The goal of the challenge is to identify unique solutions which can make life easier for people with diabetes. Anyone with an idea can apply – whether researcher, healthcare professional, start-up or person living with diabetes. We want to hear from you!​

          In 2024, two US-based innovators and four innovators from the rest of the world will be selected to pitch their final ideas at the grand DCB Start-Up Night in Berne, Switzerland, on 3 October 2024. Additionally, all finalists have the opportunity to present their ideas at the Diabetes Technology Meeting in the US on 15–17 October 2024.​ ​

          Save the dates and seize the opportunity to watch your idea become reality: www.dcberne.com/en/innovation-challenge

          More recent news

          Meet us at ATTD!

          Meet us at ATTD!

          The ATTD congress in Barcelona is just around the corner and different members of the DCB team will be on-site. Meet...

          Sign up for our newsletter
          to receive the latest news.

          * Pflichtfelder
          DSGVO *

          But could the same data tell us much more about a person's health than we currently realise?

          A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

          What did the researchers discover?

          The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

          Particularly interesting were the findings among people living with type 2 diabetes.

          The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

          For example:

          • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
          • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

          The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

          Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

          The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

          From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

          From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

          What could this mean for diabetes care?

          Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

          By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

          In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

          The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

          A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

          In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

          Projections to 2050

          Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

          For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

          Why is incidence rising?

          T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

          • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
          • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
          • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
          • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
          • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

          The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

          Implications for the next decade

          Three practical implications stand out for health systems, innovators and the diabetes community:

          • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
          • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
          • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

          At DCB, we see these trends as both a warning and a call to action.

          The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

          Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

            Selected sources

            GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

            International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

            Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

            Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

            Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

            Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

            Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

            Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

            Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

            Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

            Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

            D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

            Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

            Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

            Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

            Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


            We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


            An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

            This post was previously published in Linkedin. Click here to see the original publication.

            DCB Research AG

            Freiburgstrasse 3
            3010 Bern
            Schweiz

            “Day of the Sick” 2024 – Diabetes Centre Berne host of President Amherd’s speech 

            “Day of the Sick” 2024 – Diabetes Centre Berne host of President Amherd’s speech 

            “Day of the Sick” 2024 – Diabetes Centre Berne host of President Amherd’s speech 

            Bern, 4 March 2024 – Yesterday was the 85th anniversary of Switzerland’s oldest Disease Awareness Day, the “Day of the Sick”. The aim is to raise public awareness of health and disease issues. The President of the Swiss Confederation gives a speech at this event, which this year was held at the Diabetes Centre Berne (DCB).

            “Strengthening confidence” is the motto of this year’s “Day of the Sick”. In connection with this and as a strong player in innovation and research in the field of diabetes technology, the Diabetes Center Berne had the honour of hosting this year’s speech by the President of the Swiss Confederation, Viola Amherd. Supplemented by two statements from the DCB, from the perspective of people with diabetes, the President addressed the influence of collaboration and innovative technologies as well as the situation of carers and patients. 

            “I had to prick my finger around 60,000 times to measure my blood sugar level. You can still see the traces of this on my fingertips today. Now I have a sensor on my arm that continuously measures my blood glucose level. This technological innovation has not only given me back valuable time, but also a lot of quality of life,” summarises Maren Schinz, Innovation Manager at the DCB, who has type I diabetes. 

            The CEO of the DCB, Derek Brandt, adds: “Here at the Diabetes Centre Berne, we exchange ideas and develop new technologies. Our aim is to use new approaches to give people with diabetes back their freedom so that other areas of their lives can be given more space again.” 

            Watch the recording now:

            About DCB 
            The Diabetes Center Berne (DCB) is a private, independent Swiss foundation established in 2017 with the aim of making life with diabetes easier. DCB supports ideas and projects in the field of diabetes technology worldwide by providing expertise, access to clinical research facilities and its own laboratories as well as financial resources. The aim is to work in partnership to bring them a big step closer to market entry. The work of the DCB is not profit-orientated – the goal is new findings and innovations in diabetes management as well as a lively community. 


            About “Day of the Sick” 
            The “Day of the Sick” is a non-profit organisation that was founded in 1939. Its members include patient organisations as well as health leagues, industry and professional associations, the Swiss Conference of Cantonal Health Directors (GDK) and other associations and federations active in the healthcare sector.  
            Once a year, the “Day of the Sick” sensitises the population to a special topic in the area of health and illness. It aims to help promote relationships between the sick and the healthy, create understanding for the needs of the sick and remind people of the duties of the healthy towards the sick. It is also committed to recognising the activities of all those who work professionally and privately on behalf of patients and the sick. 

            Media Contacts

            Diabetes Center Berne


            Freiburgstrasse 3
            CH-3010 Berne
            www.dcberne.com

            Media Contact

            Sunjoy Mathieu
            sunjoy.mathieu@dcberne.com

            Office Day of the Sick

            c/o Nicole Fivaz
            Hangweg 22
            CH-3125 Toffen
            www.tagderkranken.ch

            Media Contact

            Nicole Fivaz
            info@tagderkranken.ch

            Meet us at ATTD!

            Meet us at ATTD!

            The ATTD congress in Barcelona is just around the corner and different members of the DCB team will be on-site. Meet...

            Sign up for our newsletter
            to receive the latest news.

            * Pflichtfelder
            DSGVO *

            But could the same data tell us much more about a person's health than we currently realise?

            A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.

            What did the researchers discover?

            The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.

            Particularly interesting were the findings among people living with type 2 diabetes.

            The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.

            For example:

            • Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
            • High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.

            The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.

            Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.

            The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.

            From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

            From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with

            What could this mean for diabetes care?

            Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.

            By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.

            In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

            The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.

            A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.

            In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.

            Projections to 2050

            Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.

            For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.

            Why is incidence rising?

            T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:

            • Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
            • Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
            • Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
            • Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
            • Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.

            The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.

            Implications for the next decade

            Three practical implications stand out for health systems, innovators and the diabetes community:

            • Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
            • Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
            • We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.

            At DCB, we see these trends as both a warning and a call to action.

            The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.

            Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.

              Selected sources

              GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext

              International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/

              Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918

              Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/

              Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105

              Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/

              Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578

              Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data

              Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662

              Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922

              Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/

              D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/

              Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/

              Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/

              Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/

              Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/


              We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.


              An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.

              This post was previously published in Linkedin. Click here to see the original publication.

              DCB Research AG

              Freiburgstrasse 3
              3010 Bern
              Schweiz




