There are various pieces that make up the puzzle of our vision and mission but it all boils down to one thing
Making life better for people with diabetes

Participate in the TIMES Study
The TIMES study is being conducted by the Diabetes Center Berne (DCB) and aims to gain a better understanding of type 1 diabetes (T1D) throughout the menstrual cycle.

Driving diabetes technology innovation
DCB supports the development of new innovations and products worldwide by providing expertise, access to clinical research facilities and financial resources. Watch how we aim to foster new technologies.

The latest

New endowed lectureship investigates the role of the gut microbiome in obesity and diabetes
Thanks to the support of the Diabetes Center Berne (DCB), the University of Bern is establishing a new endowed...

Four DCB professorships advance research in diabetes technology
32 publications, 37 conference contributions and over CHF 6 million in research funding: the four professorships at...
SNAQ Launches the First AI Nutritionist for CGM Users Managing Diabetes
SNAQ has announced the release of its AI Nutritionist, a first-of-its-kind digital companion designed to help people...
But could the same data tell us much more about a person's health than we currently realise?
A new study published in npj Digital Medicine suggests that looking beyond individual glucose readings could reveal patterns associated with diabetes-related health risks. The findings point towards an interesting possibility: CGM technology may one day help us understand glucose levels, and also identify individual risk profiles and support more personalised diabetes care.
What did the researchers discover?
The researchers analysed CGM data from 90,757 participants in the iCanNet cohort, including people with normoglycemia, prediabetes, type 1 diabetes and type 2 diabetes. Rather than looking at individual glucose values alone, they examined 48 different CGM-derived metrics, including glucose variability and patterns over time. Their analysis revealed distinct glucose patterns across the different groups. Combining several metrics also improved the researchers' ability to distinguish between them.
Particularly interesting were the findings among people living with type 2 diabetes.
The researchers identified four distinct glycemic phenotypes – different patterns of glucose levels and fluctuations – associated with varying risks of diabetes-related complications.
For example:
- Sustained high glucose levels were associated with a 59% higher relative risk of acute complications.
- High glucose variability was associated with a 75% higher relative risk of acute complications and a 41% higher relative risk of chronic complications.
The researchers also developed a Digital Glycemic Risk Score (DGRS), combining multiple CGM metrics to identify people with potentially elevated risks.
Among participants with type 2 diabetes who had already achieved a Time in Range of at least 70%, the model reclassified 25% into a high-risk category for acute complications and 22.3% into a high-risk category for chronic complications. These were classifications generated by the model, not confirmed predictions of complications occurring in these individuals.
The findings suggest that combining different glucose patterns may reveal information about health risks that commonly used CGM metrics alone do not fully capture.
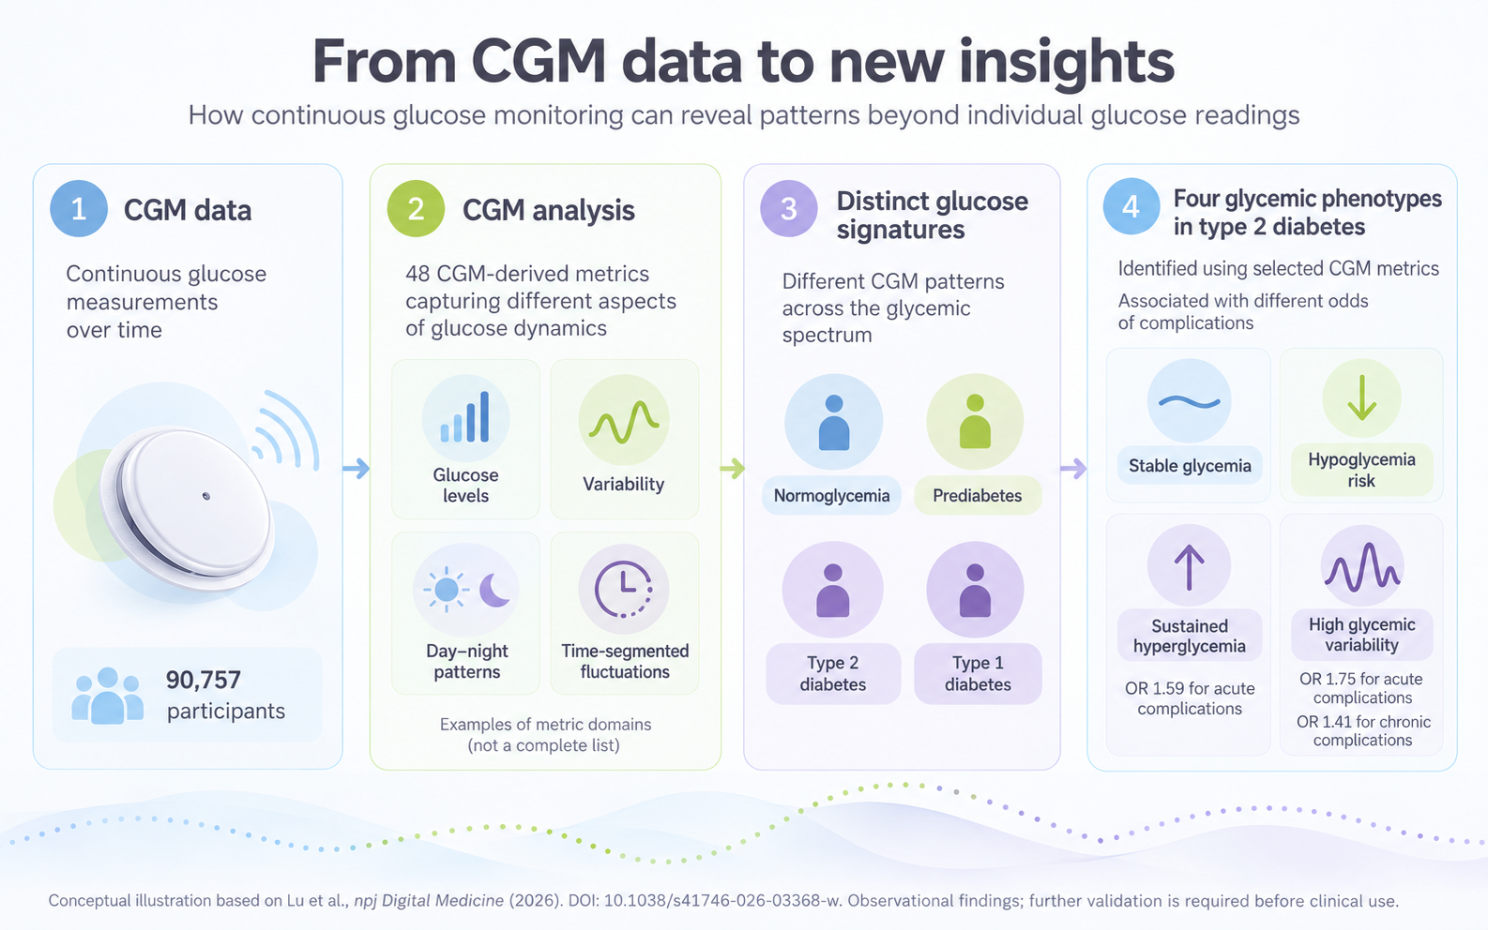
From CGM data to new insights. The study analysed 48 CGM-derived metrics from 90,757 participants and identified distinct glucose patterns across the diabetes spectrum. Among people with type 2 diabetes, four glycemic phenotypes were associated with
What could this mean for diabetes care?
Today, CGM systems primarily help people understand what is happening with their glucose levels and respond accordingly. But the enormous amount of data these devices generate may hold additional information that we are only beginning to explore.
By analysing glucose patterns over time, researchers may be able to develop digital biomarkers – measurable indicators derived from digital health data – that could help characterise individual metabolic profiles and identify potential health risks.
In the future, this could support healthcare professionals in recognising people who may benefit from closer monitoring or more personalised treatment approaches.

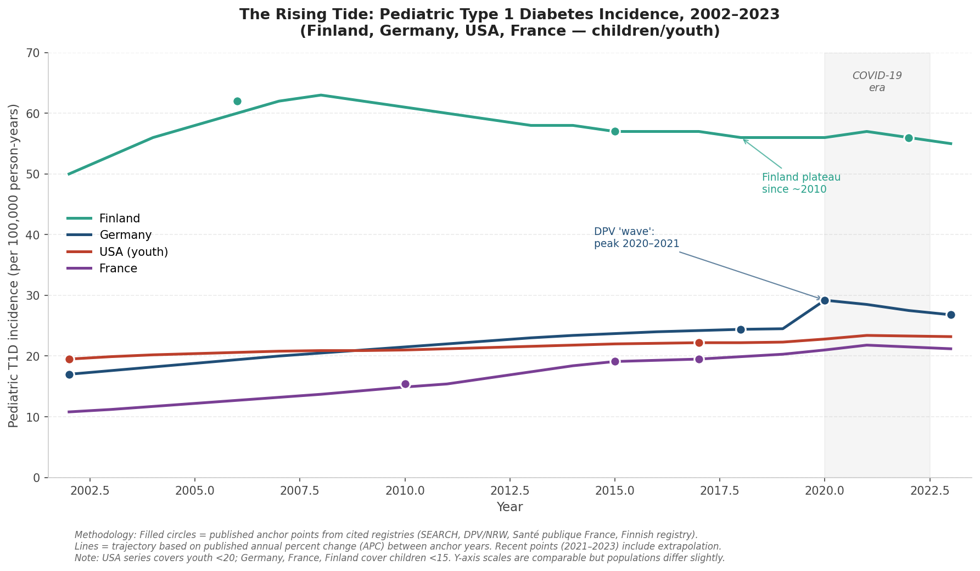
The Nordic region remains the global hotspot for childhood‑onset T1D. Finland has historically reported the highest incidence worldwide – around 60 per 100,000 children per year – although this rate appears to have stabilised or slightly declined since the early 2000s. Sweden, Norway and Denmark follow closely, and the IDF Diabetes Atlas 11 still places Finland, Sweden and Norway among the global top ten for published incidence.
A 2024 systematic review of European paediatric data (1994–2022) confirmed that the Nordic countries retain the highest absolute incidence in Europe, even as their rate of increase has slowed relative to the rapid rise in previously low‑incidence Central and Eastern European countries. A Swedish nationwide cohort study of 2.9 million children found that the heritability of childhood‑onset T1D has remained high and stable at around 0.83 over 30 years, implying that known environmental factors explain less than 10% of the observed rise.
In France, Santé publique France reports an annual T1D incidence increase of approximately 4%. Paediatric incidence rose from 15.4 to 19.1 per 100,000 person‑years between 2010 and 2015, with an overall rate of 19.5 per 100,000 in 2015–2017 and substantial regional variation. Sardinia (Italy) now reports the world’s highest published paediatric incidence at 76.3 per 100,000 (2022), having overtaken Finland, while the United Kingdom and Ireland also remain in the global top ten.
Projections to 2050
Two major modelling efforts suggest the same direction of travel. The GBD 2021 study projects that age‑standardised global type 1 diabetes prevalence will rise by about 23.9% between 2021 and 2050, a smaller relative increase than for type 2 diabetes, but a substantial absolute rise given the lifelong management burden of T1D. The IDF Diabetes Atlas 11 projects that overall adult diabetes prevalence (type 1 and type 2) will grow from 589 million in 2024 to around 853 million by 2050, a 46% absolute increase. While most of this growth is driven by type 2 diabetes, T1D contributes meaningfully through sustained or rising incidence in high‑income countries and improved survival, which increases prevalence even if incidence stabilises.
For the U.S., a modelling exercise based on SEARCH data suggests that, under a linear‑increase scenario, the number of young people with T1D could nearly triple by 2050, with the steepest relative growth among Hispanic and Black children.
Why is incidence rising?
T1D is a polygenic autoimmune disease in which environmental triggers act on a susceptible genetic background. Several, often overlapping, hypotheses are under investigation:
- Reduced early‑life exposure to common infections (“hygiene hypothesis”), with mixed evidence.
- Rising childhood adiposity and insulin resistance, which may accelerate the clinical presentation of existing islet autoimmunity (“accelerator hypothesis”).
- Viral triggers such as enteroviruses and, more recently, SARS‑CoV‑2, where meta‑analyses report a 14–27% increase in paediatric T1D incidence during the pandemic.
- Dietary and microbiome‑related factors, including early cow’s‑milk exposure, gluten timing and shifts in the infant gut microbiome.
- Vitamin D status and latitude, endocrine‑disrupting chemicals, pollution and perinatal factors such as higher maternal age, higher birth weight and Caesarean delivery.
The Swedish cohort study mentioned above is a stark reminder of how much remains unexplained: even with population‑wide data on several environmental exposures, less than 10% of the rise in T1D incidence in Sweden could be attributed to known factors. This underscores the need for long‑term birth cohorts, population‑level islet‑autoantibody screening and mechanistic immunology.
Implications for the next decade
Three practical implications stand out for health systems, innovators and the diabetes community:
- Health systems need to prepare for more people living with type 1 diabetes. Even under conservative assumptions, the number of people living with type 1 diabetes will continue to rise. This has practical consequences for insulin and sensor supply, reimbursement for diabetes technology, specialist care and clinical-trial infrastructure.
- Early detection is becoming more relevant. Type 1 diabetes can often be detected before symptoms appear, through markers of early autoimmune activity. With the first therapy now approved to delay clinical onset in people at an early disease stage, screening is no longer only a research question. Programmes such as Fr1da in Germany and the D1Ce trial in Italy show how early identification could inform future intervention strategies.
- We still need to understand why incidence is rising. Many environmental factors are being studied, but no single explanation is sufficient. Until we better understand the drivers behind the increase, true primary prevention will remain out of reach. This makes high-quality registries, long-term cohort studies and coordinated research more important than ever.
At DCB, we see these trends as both a warning and a call to action.
The rising incidence of type 1 diabetes will require sustained collaboration between clinicians, researchers, industry, policymakers and crucially people living with diabetes and their families.
Our work in innovation, clinical research infrastructure and community engagement aims to contribute to that collective effort.
Selected sources
GBD 2021 Diabetes Collaborators. Global, regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050. The Lancet, 2023. https://www.thelancet.com/article/S0140-6736(23)01301-6/fulltext
International Diabetes Federation. IDF Diabetes Atlas, 11th edition. 2025. https://diabetesatlas.org/
Ogle GD, et al. Global type 1 diabetes prevalence, incidence, and mortality estimates 2025: Results from the IDF Atlas 11 and the T1D Index v3.0. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725002918
Stahl-Pehe A, et al. Wave in Pediatric Type 1 Diabetes Incidence After the Emergence of COVID-19: Peak and Trough Patterns in German Youth — DPV Registry. Diabetes Care, 2025. https://diabetesjournals.org/care/article/48/4/e47/157803/
Buchmann M, et al. Type 1 diabetes incidence curves differ by age for girls and boys between 1996 and 2022: Results from the North Rhine-Westphalia Diabetes Registry. Diabetes Research and Clinical Practice, 2025. https://www.sciencedirect.com/science/article/pii/S0168822725000105
Nagl K, et al. Ongoing Increase in Incidence of Diabetes in Austrian Children and Adolescents 1989–2021. Pediatric Diabetes, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12017070/
Schoenle EJ, et al. Epidemiology of Type I diabetes mellitus in Switzerland: Steep rise in incidence in under-5 year old children in the past decade. Diabetologia, 2001. https://www.researchgate.net/publication/12017578
Santé publique France. Diabetes — Data. Updated 2024. https://www.santepubliquefrance.fr/en/diabete/data
Piffaretti C, et al. Trends in childhood type 1 diabetes incidence in France, 2010–2015. Diabetes Research and Clinical Practice, 2018. https://www.sciencedirect.com/science/article/abs/pii/S0168822718304662
Ruiz-Grao MC, et al. Trends in the Incidence of Type 1 Diabetes in European Children and Adolescents from 1994 to 2022: A Systematic Review and Meta-Analysis. Pediatric Diabetes, 2024. https://onlinelibrary.wiley.com/doi/10.1155/2024/2338922
Ji J, et al. Stable heritability of type 1 diabetes in a Swedish Nationwide Cohort Study. Nature Communications, 2024. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC12174315/
D’Souza D, et al. Incidence of Diabetes in Children and Adolescents During the COVID-19 Pandemic: A Systematic Review and Meta-Analysis. JAMA Network Open, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10314307/
Quinn LM, et al. Environmental Determinants of Type 1 Diabetes: From Association to Proving Causality. Frontiers in Immunology, 2021. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8518604/
Esposito S, et al. Changes in the Global Epidemiology of Type 1 Diabetes in an Evolving Landscape of Environmental Factors. International Journal of Molecular Sciences, 2023. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10141720/
Rogers MAM, et al. Fluctuations in the incidence of type 1 diabetes in the United States from 2001 to 2015: a longitudinal study. BMC Medicine, 2017. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5688827/
Imperatore G, et al. Projections of Type 1 and Type 2 Diabetes Burden in the U.S. Population Aged <20 Years Through 2050. Diabetes Care, 2012. https://pmc.ncbi.nlm.nih.gov/articles/PMC3507562/
We hope this overview is helpful for your own work in diabetes care, research or advocacy. As always, we are grateful for your interest in and support of our activities and we look forward to continuing this conversation with you in future editions of our “DID YOU KNOW…” series.
An earlier version of this article was originally published in the private newsletter of our CEO, Derek Brandt here: Diabetes Technology News.
This post was previously published in Linkedin. Click here to see the original publication.


DCB Research AG
Freiburgstrasse 3
3010 Bern
Schweiz